
Therapist practice · Updated 2026-11-09
GIRP Notes for Therapists: Template, Examples and Checklist (Free Printable)
Ready-made printable: Therapy Progress Notes and Intake Templates Fillable PDF, 20 pages: SOAP, DAP and BIRP notes, intake, treatment plan and safety plan
Holiday 20% off: about $7.36, was $9 (EUR 8) · instant digital download
Try it free first: download a fillable sample (SOAP note and DAP note, PDF, 226 KB). Type into it on screen, then get the full pack. No email needed.

A GIRP note starts where a reviewer starts: with the treatment plan. Its first heading is the goal you worked on, so before anyone reads a word about the session they already know why it happened. Then come the three parts every useful progress note needs: what you did, how the client responded, and what happens next. That simple reordering is why some US agencies, programs and insurance based practices ask clinicians to write GIRP, and why it can make medical necessity easier to show than a format that leaves the plan link for later.
This guide is for counselors, therapists, social workers, psychologists, school counselors and trainees in the US. It explains what goes in each section of a GIRP note, how GIRP compares with BIRP, SOAP and DAP, how to turn a fuzzy treatment goal into an objective a note can actually track, and how to write a GIRP note step by step. Then it walks through five complete fictional examples: adult social anxiety, a child session with a parent check in, motivational work on alcohol use, a teen in a family session, and a stuck case where the plan has to change. After that come the words worth swapping out, how GIRP notes support medical necessity, the privacy basics, common mistakes, and a free three page printable: a blank GIRP template, a filled example and a before you sign checklist.
Jump to the free GIRP note template
This is educational information for licensed clinicians and trainees, not legal, billing or clinical advice. Documentation rules differ by state, license, setting and payer. Check your state board, your agency policy, your payer contracts and your supervisor's guidance if you are pre-licensed. Every client, clinician and session on this page is fictional.
What GIRP stands for
GIRP stands for Goal, Intervention, Response, Plan. You will also see it written as Goals, Interventions, Response, Plan; the content is the same. Each section answers one question.
| Section | Question it answers | What usually goes in it |
|---|---|---|
| G: Goal | Which part of the treatment plan did this session serve, and where is the client on it today? | The goal and objective by number, in the plan's wording, followed by the client's current status on it: what they reported since last session, what you observed, and any measure given today with its score and the previous score. |
| I: Intervention | What did you do to move that objective? | The techniques, skills, modality and activities you used, described concretely enough that another clinician could picture the session, and tied back to the objective. |
| R: Response | How did the client respond, and did the objective move? | Engagement, insight, emotion, skill use, ratings before and after an exercise, barriers, and a clear statement of progress on the objective: met, progressing, no change or worse. |
| P: Plan | What happens next? | Homework, the focus of the next session, the next appointment and frequency, referrals and coordination of care, any safety steps, and any change to the treatment plan. |
The important detail is that the G section is not only a copy of the goal. A note that says "Goal: reduce anxiety" and then jumps to the intervention has lost the picture of the client that day. Good GIRP notes put two things under G: the objective you worked on, and where the client stands on it right now. That second part does the job that Behavior does in a BIRP note, Subjective and Objective do in SOAP, and Data does in DAP.
Why a goal first note helps
Most progress note formats make the reader hunt for the link between the session and the plan. GIRP puts it on the first line. That has a few practical effects.
- Medical necessity is visible immediately. A reviewer reading a GIRP note can see which documented problem the session addressed without reading the whole note.
- It keeps sessions on purpose. When you know you will have to write the goal first, you tend to plan the session around it, and it becomes obvious when several sessions in a row have drifted away from the plan.
- Progress is easier to track across notes. If every note names objective 2.1 and marks progress on it, ten notes later you can see the trend at a glance, which makes treatment plan reviews faster.
- It forces better treatment plans. You cannot write "progress on objective 1.2: partial" if objective 1.2 is "feel better." GIRP quietly pushes you toward measurable objectives.
The cost is that a session where the client arrives in crisis, or brings something important that is not in the plan, can feel awkward to fit under a goal heading. The fix is simple: name the goal that best fits, describe what actually happened in the status lines, and say in the Plan whether the treatment plan needs to change. If a new problem keeps coming up, that is a signal to update the plan, not to stretch an old goal to cover it.
GIRP vs BIRP vs SOAP vs DAP
All four are structured progress note formats. A well written note in any of them will usually contain the same facts; the difference is what comes first and what gets its own heading.
| Format | Sections | Strength | Watch out for |
|---|---|---|---|
| GIRP | Goal, Intervention, Response, Plan | Starts from the treatment plan, so the reason for the session is clear from the first line; progress on each objective is easy to follow across notes. | The client's presentation can get squeezed out if the G section only restates the goal. Keep the status lines. |
| BIRP | Behavior, Intervention, Response, Plan | Starts from what the client brought and what you observed; interventions and response are explicit. | The plan link has to be added on purpose, usually as a goal line at the top. |
| SOAP | Subjective, Objective, Assessment, Plan | The most widely recognized format in health care; good when you share records with medical providers. | Therapists often struggle with what counts as "objective" in talk therapy, and interventions can get lost. |
| DAP | Data, Assessment, Plan | Short and flexible; puts weight on your clinical reasoning. | "Data" can turn into a session transcript, and interventions may not be named. |
SOAP comes from medicine: it grew out of the problem oriented medical record that physician Lawrence Weed described in his 1968 New England Journal of Medicine article "Medical Records That Guide and Teach." GIRP, BIRP and DAP are later adaptations used widely in behavioral health. For BIRP in depth, with five examples, see BIRP notes for therapists. For SOAP and DAP side by side, with one fictional session written both ways, see SOAP vs DAP notes for therapists.
GIRP or BIRP? They differ in only one letter, and in practice a BIRP note with a goal line at the top and a GIRP note with good status lines end up nearly identical. Choose GIRP when your agency or payer asks for it, when your work is organized around a written plan with numbered objectives, or when you want the progress trend to be the first thing a reader sees. Choose BIRP when sessions are less predictable and the client's presentation is usually the most important starting point. Whatever you choose, use one format consistently for a client so the record reads as a story.
Write goals a GIRP note can use
A GIRP note is only as good as the goal it starts from. Treatment plans usually have three layers, and GIRP notes work best when they point at the middle one.
- Problem: what is getting in the way, in functional terms. "Avoids speaking at work because of fear of judgment; passed over for a promotion."
- Goal: the broad direction. "Speak up at work."
- Objective: a specific, measurable step toward the goal, with a target and a way to know. "Speak at least once in 3 of 4 weekly team meetings, as recorded on a speaking log, by 12/31."
Objectives give the Response section something to measure against. If a note can only say "client is working on reducing anxiety," the objective is too vague. If it can say "spoke in 1 of 2 meetings this week, baseline 0 of 4," the objective is doing its job. Many clinicians use the SMART frame (specific, measurable, achievable, relevant, time bound) to write objectives; our therapy treatment plan template walks through problems, goals, SMART objectives and interventions with a filled example, and numbers the objectives so your notes can point to them.
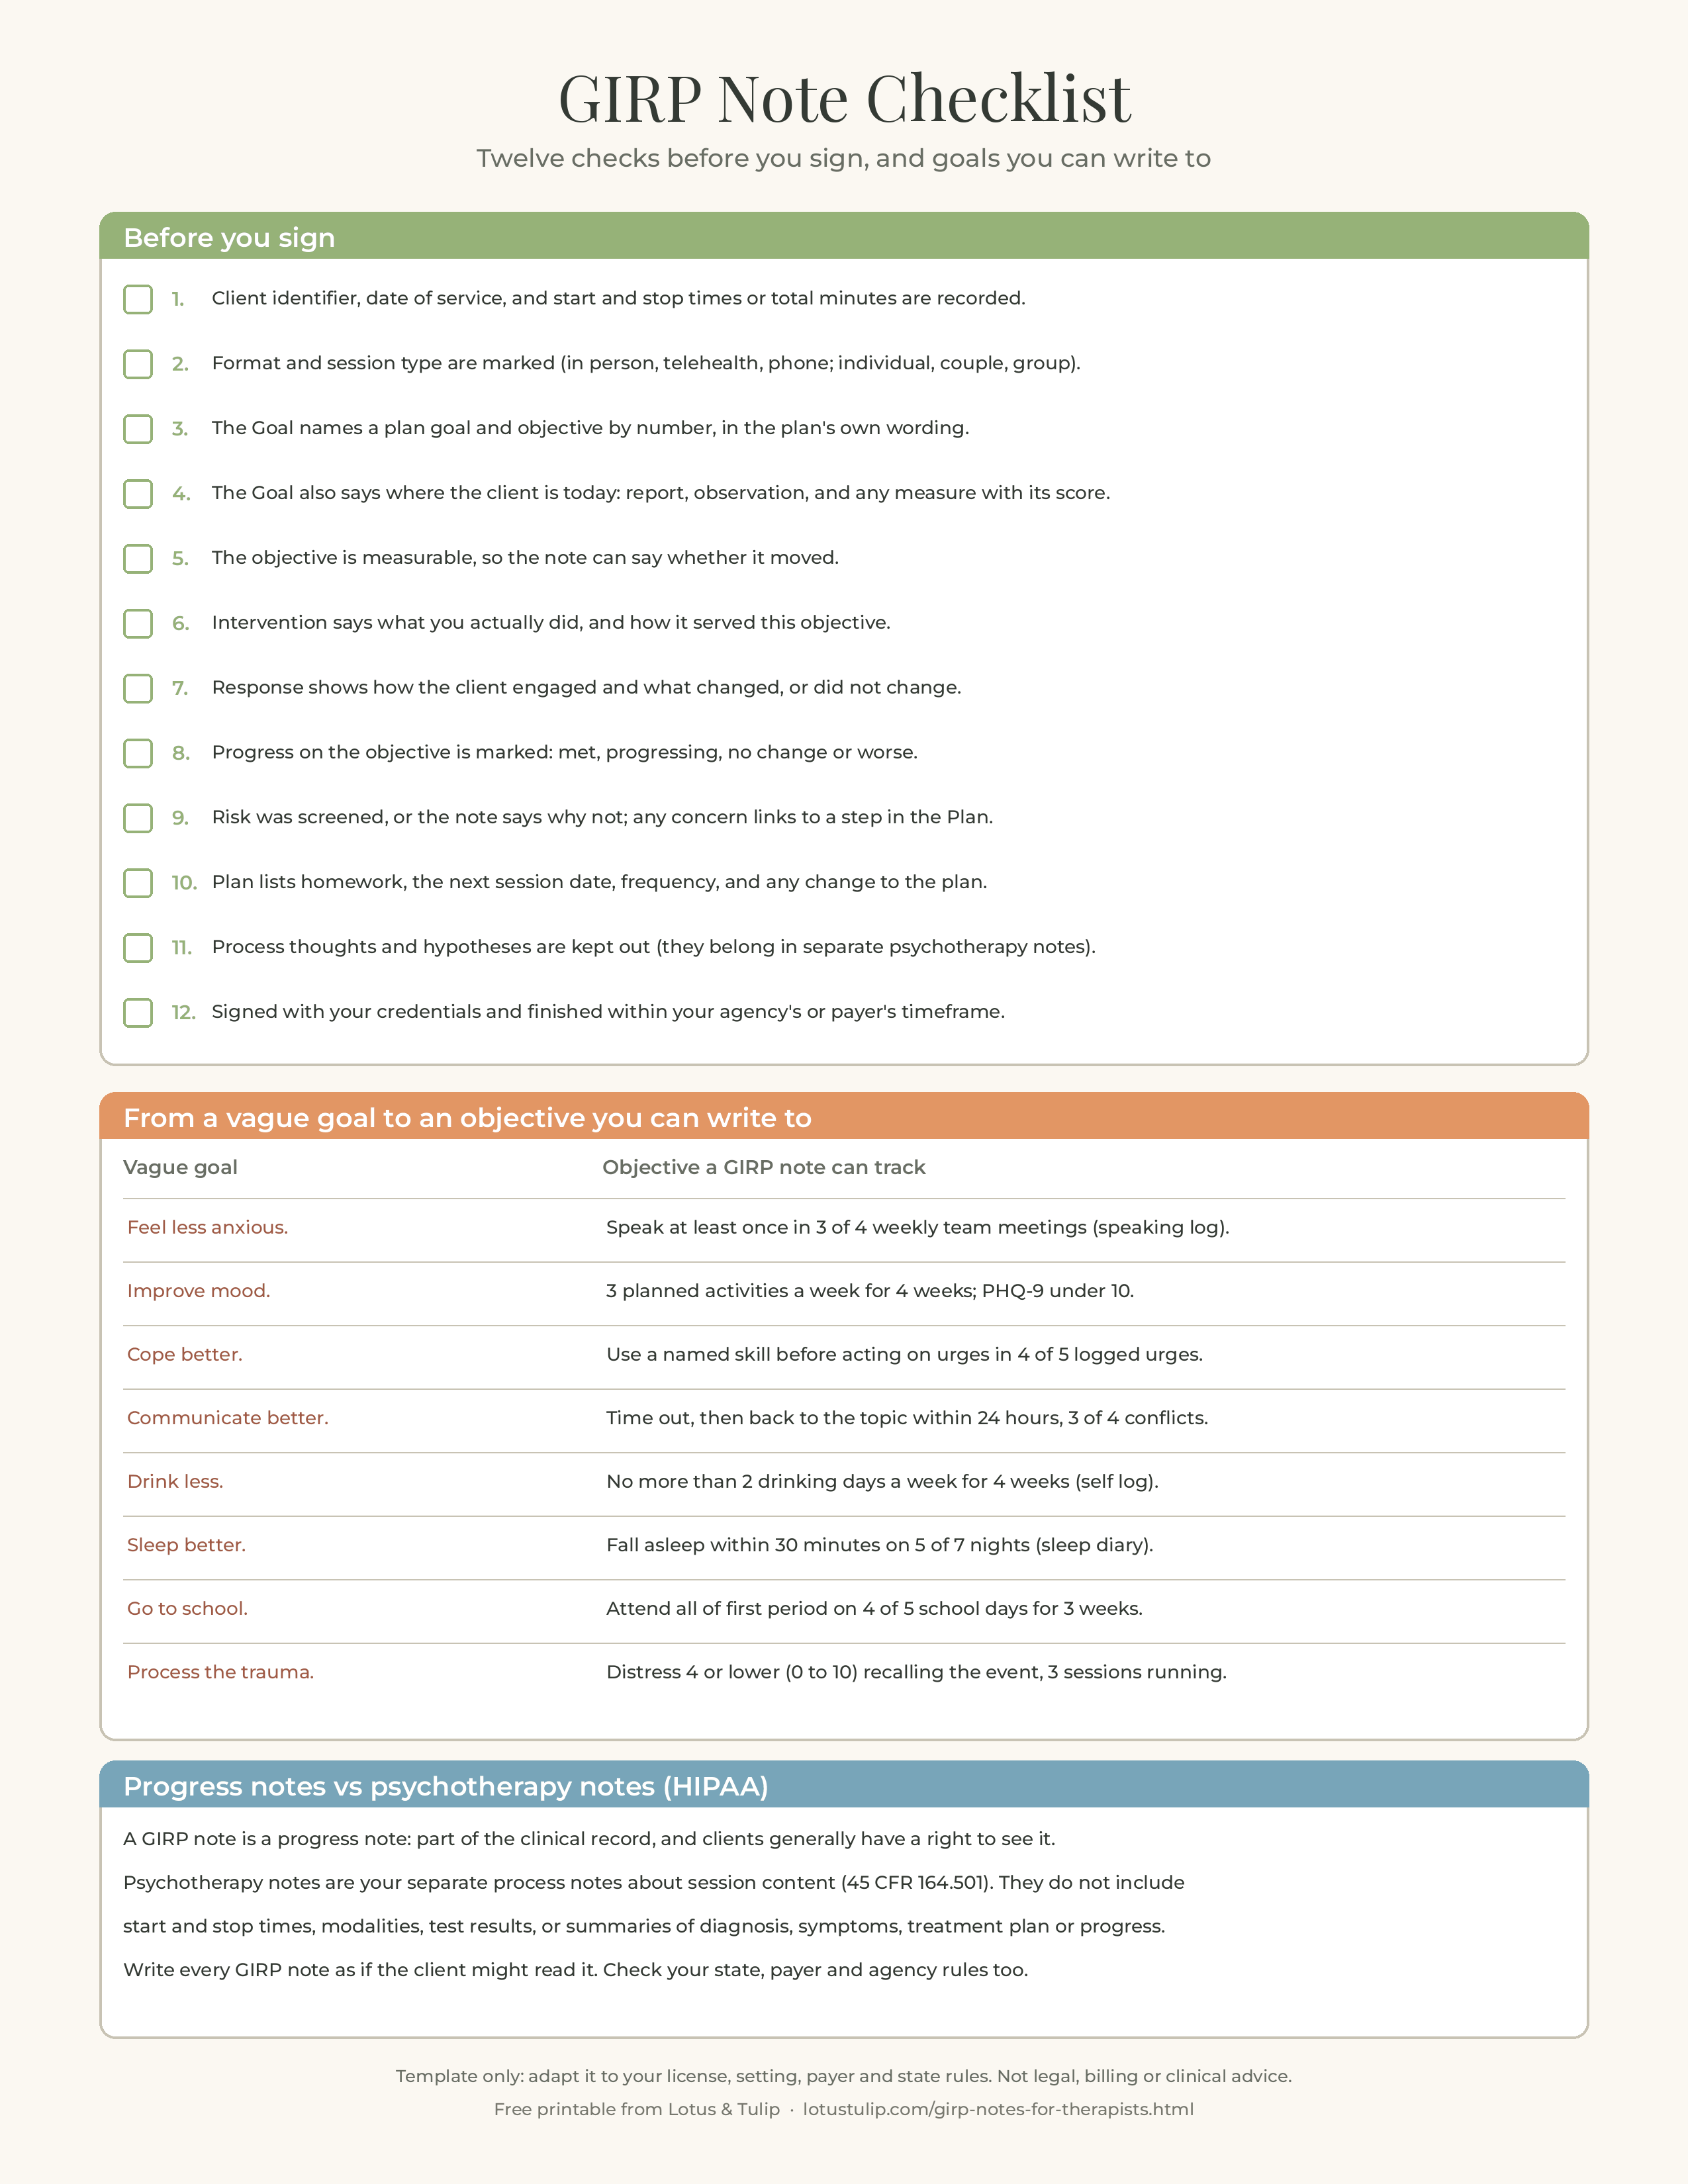
| Vague goal | Objective a GIRP note can track |
|---|---|
| Feel less anxious. | Speak at least once in 3 of 4 weekly team meetings (speaking log). |
| Improve mood. | Complete 3 planned activities a week for 4 weeks; PHQ-9 under 10 at the next plan review. |
| Cope better. | Use a named skill before acting on an urge in 4 of 5 logged urges. |
| Communicate better. | Use a time out and return to the topic within 24 hours in 3 of 4 conflicts. |
| Drink less. | No more than 2 drinking days a week for 4 consecutive weeks (self log). |
| Sleep better. | Fall asleep within 30 minutes on 5 of 7 nights (sleep diary). |
| Go to school. | Attend all of first period on 4 of 5 school days for 3 weeks. |
| Process the trauma. | Distress rating of 4 or lower (0 to 10) when recalling the event, in 3 sessions running. |
Write objectives the client would recognize. If the client helped choose the target, and you use their words where you can, the objective is more likely to matter to them, and the G line in your notes will read as their goal rather than yours.
How to write a GIRP note, step by step
- Fill in the session details first. Client name or ID, date of service, start and stop times or total minutes, format (in person, telehealth video or phone), session type (individual, couple or family, group) and who attended. Time based psychotherapy codes depend on it, so record it while it is fresh.
- Name the goal and objective. Write the goal and objective number and copy the plan's wording, for example "Goal 2: speak up at work. Objective 2.1: speak at least once in 3 of 4 weekly team meetings." If the session covered two objectives, name both.
- Add the client's status on that objective. Under the goal line, record what the client reported since last session, what you observed (appearance, mood and affect, engagement), and any measure you gave today with its score and the previous or baseline score. Use a short quote when it captures the client's view.
- Write Intervention as actions. Use verbs: reviewed, taught, modeled, rehearsed, guided, challenged, explored, reflected, assigned. Say what each technique was applied to and how it served the objective named in G.
- Write Response honestly. Describe how the client engaged and what changed during the session: ratings before and after, a new insight in their words, a skill they practiced, or a barrier described as behavior.
- Mark progress on the objective. End the Response with one clear line: met, progressing, no change or worse, with the evidence. This is the line that makes a run of GIRP notes easy to review.
- Record the risk check. Note whether risk was screened and the result, or why it was not screened today. If there is any concern, the Plan should say what you did about it.
- Write a Plan that follows from the Response. Homework, the focus for next time, the next appointment and frequency, referrals, releases and coordination of care. If the objective has been met, name the next one. If there has been no progress for several sessions, say what will change.
- Read it as an outsider, then sign. Would the client be comfortable reading it? Could a covering clinician continue the work? Could a reviewer see why the session was needed? Remove process thoughts that belong in separate psychotherapy notes, then sign with your credentials within your agency's or payer's timeframe, and use a dated addendum for anything you add later.
What goes in each section, with weak and strong lines
G: Goal
The G section has two jobs: point at the plan, and show where the client is. The first is a copy and paste from the plan; the second has to be written fresh every time.
Weak: "Goal: decrease depression."
Strong: "Goal 1: improve mood and daily functioning. Objective 1.2: complete 3 planned activities a week. Client completed 2 of 3 planned activities (activity log), up from 1 of 3 last week. Stated: 'The walk was the only thing I didn't dread.' PHQ-9 = 15 (was 18 on 10/30). Arrived on time, hair brushed, more eye contact than last session; mood 'a little lighter,' affect constricted but brightened when talking about her niece."
I: Intervention
Intervention is where many notes go vague, usually by naming a model instead of describing an action. "CBT" tells a reader very little. "Scheduled three activities for specific days and times and problem solved the barrier to the Thursday one" tells them exactly what you did and why.
Weak: "Provided CBT and support."
Strong: "Reviewed activity log against objective 1.2. Behavioral activation: linked mood ratings to completed activities, then scheduled 3 activities for specific days and times. Problem solved the Thursday barrier (no transport) by moving the activity to a walk from home."
R: Response
Response shows whether the intervention landed and whether the objective moved. It is also where you describe non engagement fairly: what the client said or did, not a label.
Weak: "Client responded well."
Strong: "Client noticed that her highest mood ratings fell on the 2 days she left the house and said, 'So the walk actually counts.' Chose the 3 activities herself. Doubted she would manage Saturday. Progress on objective 1.2: progressing (2 of 3, up from 1 of 3)."
P: Plan
Plan should be specific enough that the next session can start from it. Include homework, the next appointment and frequency, what you will review, referrals or releases, safety follow up, and any change to the objective.
Weak: "Continue per plan."
Strong: "Homework: 3 scheduled activities; rate mood before and after each on the log. Next session 11/19, in person, weekly per plan. Review log; add one social activity if 3 of 3 are completed. Repeat PHQ-9 at the 12/3 plan review."
GIRP note examples (all fictional)
Each example below is invented for illustration. Names are initials, details are made up, and none of them describes a real person. Adapt the content and length to your setting; many real notes are shorter than these.
Example 1: Adult with social anxiety (individual, in person)
Fictional. Client "J.P.," 29, individual session, in person, 3:00 to 3:50 p.m. (50 minutes), session 7.
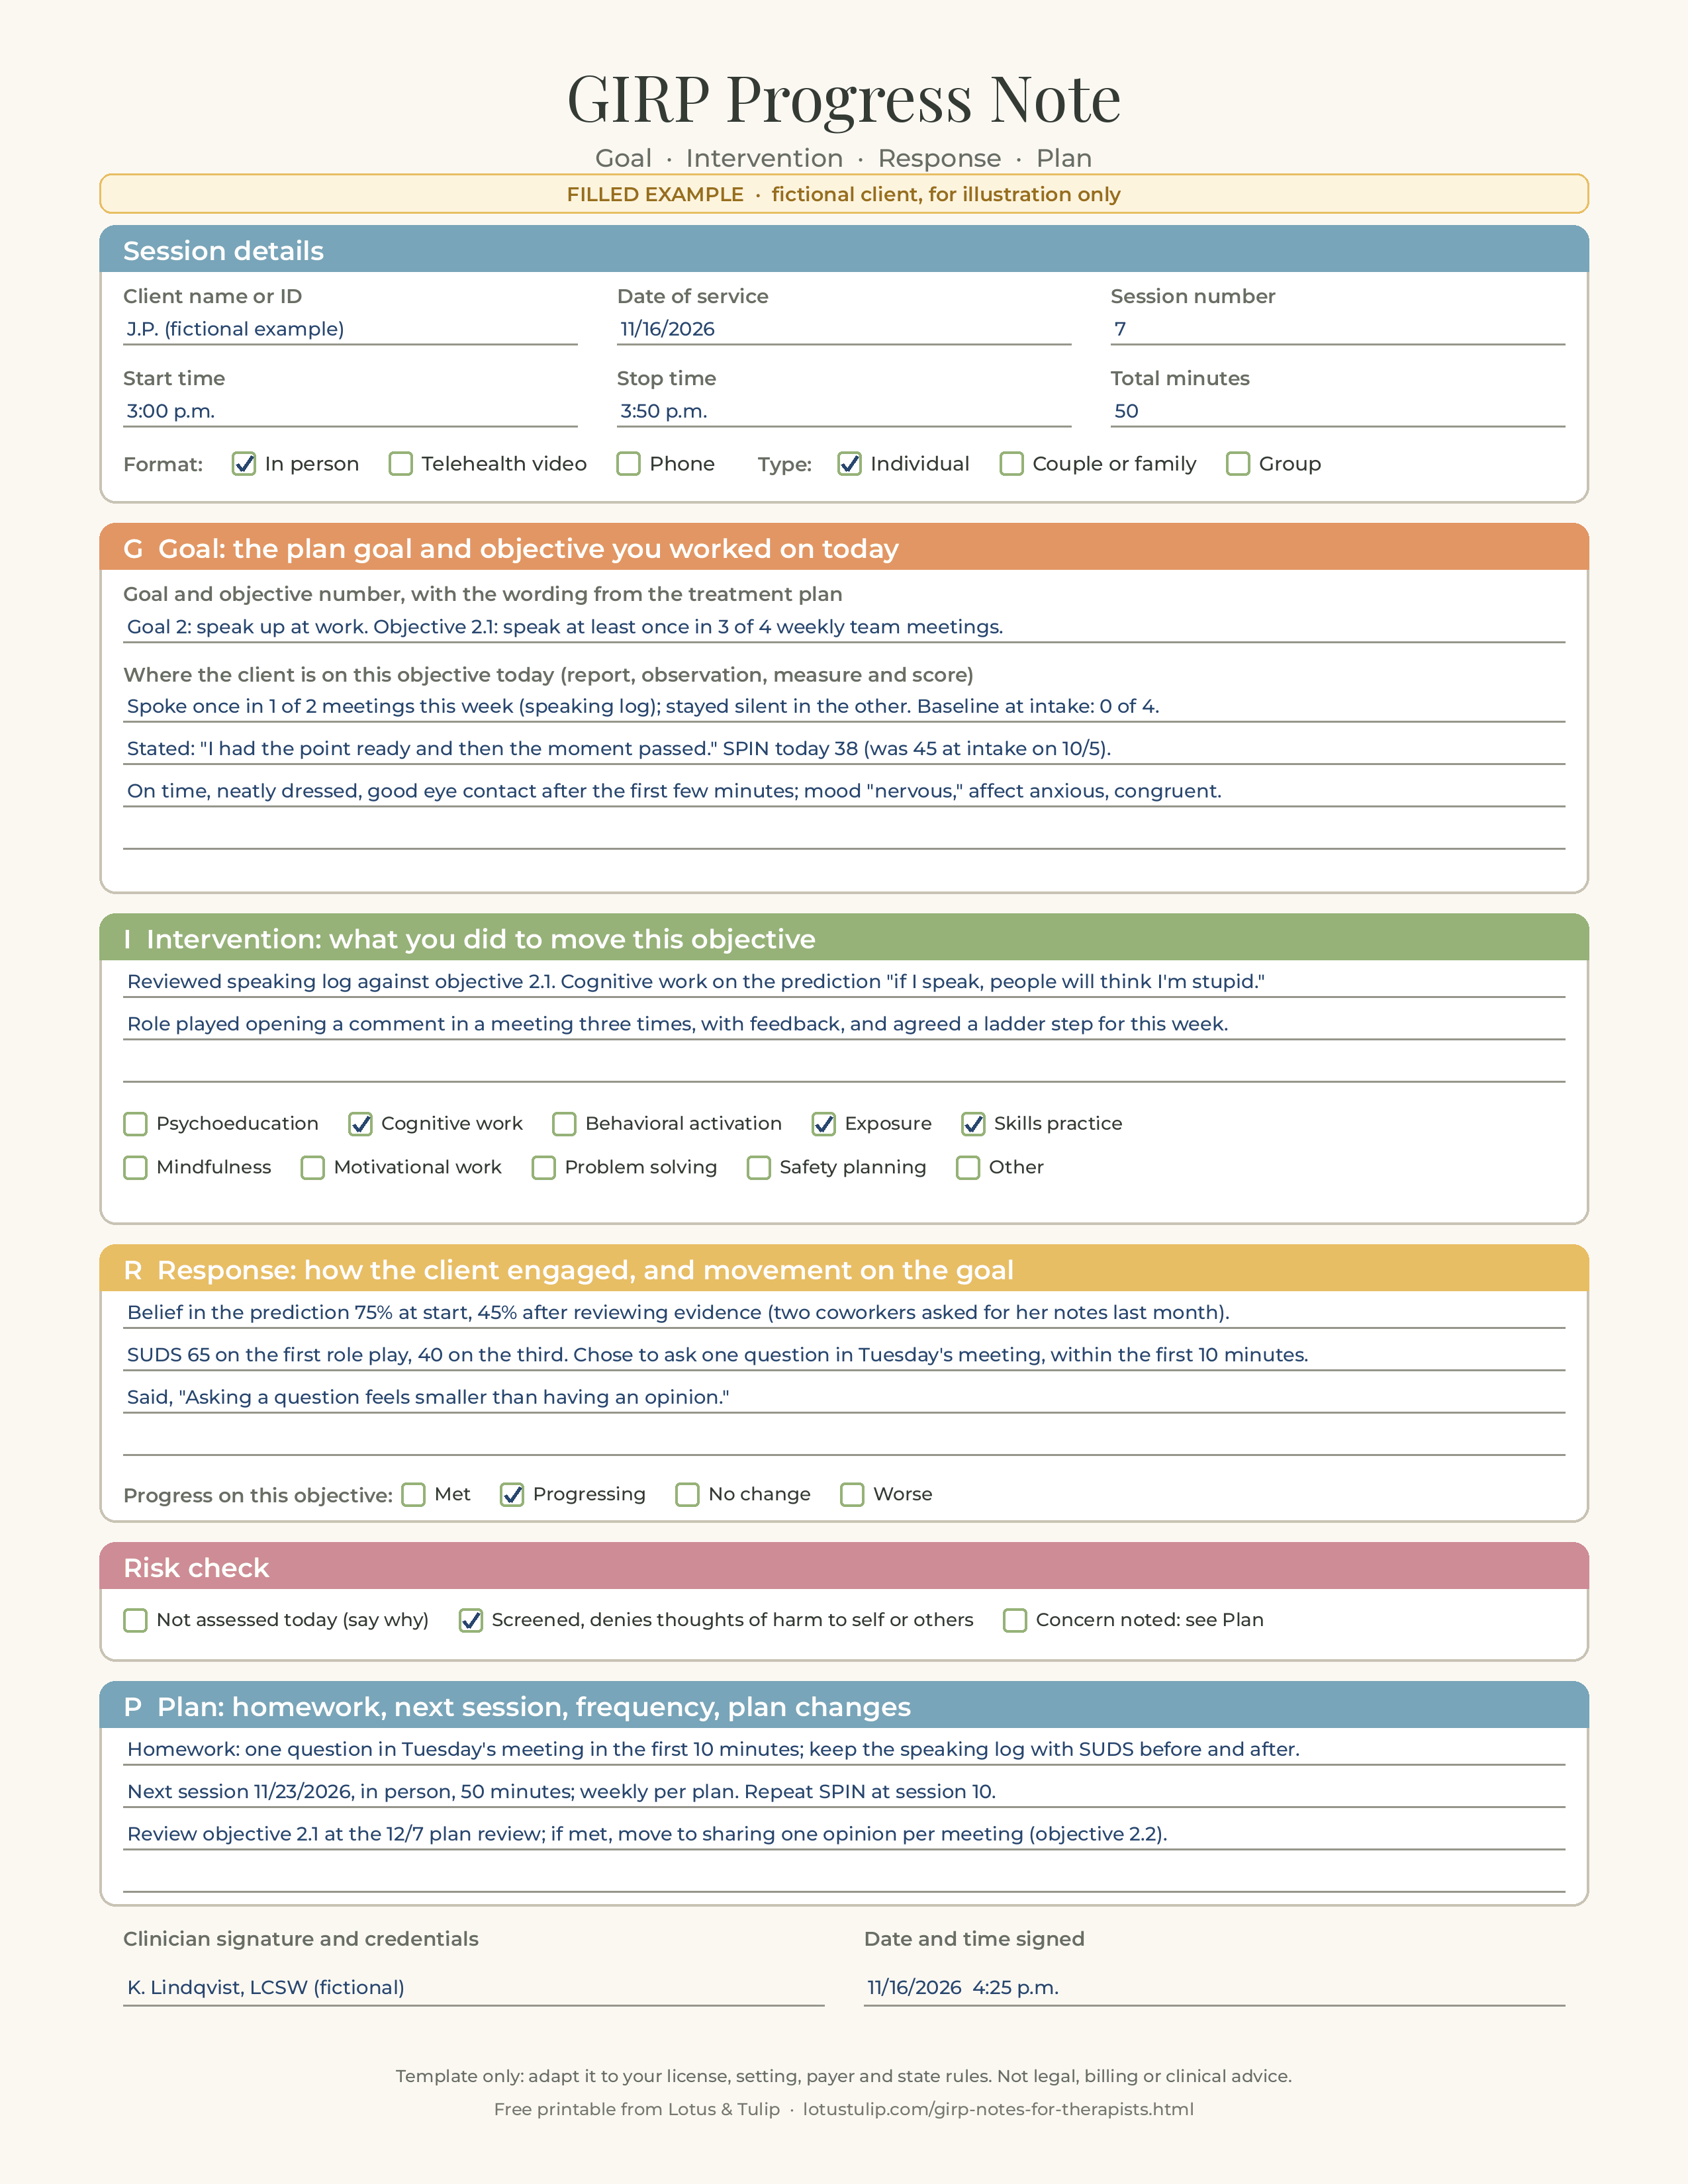
G: Goal 2: speak up at work. Objective 2.1: speak at least once in 3 of 4 weekly team meetings (speaking log). Client spoke once in 1 of 2 meetings this week and stayed silent in the other; baseline at intake was 0 of 4. Stated: "I had the point ready and then the moment passed." Social Phobia Inventory (SPIN) today 38 (was 45 at intake on 10/5). On time, neatly dressed, good eye contact after the first few minutes. Mood "nervous," affect anxious and congruent.
I: Reviewed the speaking log against objective 2.1. Cognitive work on the prediction "if I speak, people will think I'm stupid," including evidence for and against. Role played opening a comment in a meeting three times, with feedback after each. Agreed the next step on the exposure ladder.
R: Belief in the prediction moved from 75% to 45% after the client recalled that two coworkers had asked for her meeting notes last month. SUDS 65 on the first role play and 40 on the third. Chose to ask one question in Tuesday's meeting within the first 10 minutes, saying, "Asking a question feels smaller than having an opinion." Progress on objective 2.1: progressing (1 of 2 this week, baseline 0 of 4).
P: Homework: one question in Tuesday's meeting within the first 10 minutes; keep the speaking log with SUDS before and after. Next session 11/23, in person, 50 minutes, weekly per plan. Repeat SPIN at session 10. Review objective 2.1 at the 12/7 plan review; if met, move to objective 2.2, sharing one opinion per meeting.
This is the same session shown filled in on page 2 of the free printable below.
Example 2: Child anxiety session with a parent check in
Fictional. Client "E.M.," age 8, individual session with a 10 minute parent check in at the end, in person, 4:00 to 4:53 p.m. (53 minutes). The parent consented to treatment and to the check in format at intake.
G: Goal 1: manage worry at bedtime. Objective 1.1: fall asleep in own bed without a parent in the room on 5 of 7 nights (parent sleep chart). Parent's chart shows 3 of 7 nights this week, up from 0 of 7 at intake and 2 of 7 last week. E. reported that the "worry monster" was "quieter on Tuesday." Separated from parent easily in the waiting room, played readily, made eye contact. Became quiet and looked down when bedtime was mentioned.
I: Used a drawing exercise to externalize the worry ("what the worry monster says at night"). Practiced belly breathing with a stuffed animal on E.'s stomach, 3 rounds. Made a "brave bedtime" coping card with E.'s chosen words. In the parent check in, reviewed the sleep chart, coached the parent on brief, calm reassurance and on checking in at set times instead of staying in the room (objective 1.1).
R: E. drew the worry monster and wrote two of its messages ("something bad will happen," "mom will leave"). Answered back to each with a coping thought after modeling. Did the breathing and said the animal "went up and down slow." Chose "I am safe, mom is downstairs" for the coping card. Parent said she had been going back in "every time he called" and agreed to try 5 minute check ins. Progress on objective 1.1: progressing (3 of 7, last week 2 of 7).
P: Homework: coping card and 3 breaths at lights out; parent uses 5 minute check ins and keeps the sleep chart. Next session 11/18, weekly. If 5 of 7 nights are reached for 2 weeks, begin spacing check ins to 10 minutes. Discuss a school worry check in with the parent next week if daytime worry comes up again.
For a minor, state law sets who consents to treatment and who can see records. HHS explains that parents are generally the personal representatives of their minor children under HIPAA, with state law and some exceptions deciding the details. Check your state's rules and agree with the family at intake what you will share from individual time.
Example 3: Alcohol use and motivational work (outpatient)
Fictional. Client "R.D.," 52, individual session, telehealth video, 8:00 to 8:55 a.m. (55 minutes). Client confirmed he was at home in a private room and gave a callback number. Plan: Goal 1, reduce alcohol use and its effect on work and family.
G: Goal 1, objective 1.1: no more than 2 drinking days a week for 4 consecutive weeks (self log). Client logged 4 drinking days this week (last week 3), including one evening of 7 drinks after an argument with his adult son. Stated: "I know what you're going to say. I just didn't care that night." AUDIT-C today 9 (was 10 at intake). Alert, tired, sitting forward, speech normal. Mood "annoyed at myself," affect irritable early, softer later in session.
I: Motivational interviewing: reflected the client's frustration without arguing, explored his own reasons for change, and used a 0 to 10 importance and confidence ruler. Reviewed the drinking day after the argument as a chain (trigger, thoughts, urge, drink) and identified one point where a different choice was possible. Asked permission before offering two options for the next argument (objective 1.1).
R: Rated importance 8 and confidence 4. When asked why confidence was not lower, said, "Because I did have two dry weekends last month." Named the moment he got the car keys to drive to the store as the point where he could have called his brother. Chose to text his brother after any argument before deciding whether to drink. Denied withdrawal symptoms on the agency's standard questions. Progress on objective 1.1: no change (4 days this week, target 2 or fewer).
P: Homework: continue the drinking log, adding a line for arguments and what he did next; text his brother after any argument. Next session 11/16, telehealth, weekly. With the client's agreement, discuss at the next session whether to invite his wife to one session. Repeat AUDIT-C at the 12/1 plan review; if there is no progress by then, review the level of care and medication options with the client and, with a signed release, his primary care provider.
If you work in a federally assisted substance use disorder program, its records are also protected by 42 CFR Part 2, which has its own consent and disclosure rules on top of HIPAA. See the privacy section below.
Example 4: Teen depression in a family session
Fictional. Client "S.B.," 15, family session with the client and both parents, in person, 6:00 to 6:55 p.m. (55 minutes). Individual sessions alternate with family sessions per the plan.
G: Goal 3: reduce conflict at home about school. Objective 3.1: family holds a 15 minute weekly planning talk with no raised voices in 3 of 4 weeks (family report). Family reported one planning talk this week; it ended early when voices were raised over a missing assignment. S. stated: "They only talk to me when something's wrong." Mother stated: "We don't know what else to do when the school emails." S. sat apart from parents, arms crossed, short answers for the first 20 minutes, then joined in. Parents spoke quickly and over each other early on.
I: Set a simple talking order with a one person at a time rule. Reflected each person's concern and summarized the shared goal (S. passing the semester with fewer fights). Coached the parents to open the weekly talk with one thing that went well before any school item. Rehearsed the first 5 minutes of the next planning talk in session (objective 3.1).
R: S. uncrossed her arms when her father named something that had gone well ("you made dinner Tuesday"). In the rehearsal, both parents opened with a positive and S. offered, unprompted, to check the school portal with them on Sundays. Mother said the talking order "made it calmer than our kitchen." Progress on objective 3.1: no change yet (0 of 1 talks without raised voices), with a concrete plan agreed.
P: Homework: one 15 minute planning talk on Sunday using the agreed order, opening with one positive each. Next individual session with S. on 11/17; next family session 11/24. In S.'s individual session, review the PHQ-A trend and her own goals for the family talks.
With teens, agree at the start what you will and will not share with parents from individual sessions, within the limits of your state law and safety duties, and write family session notes so that every family member could read them without being blamed by them.
Example 5: A stuck case and a plan change
Fictional. Client "M.A.," 41, individual session, telehealth video, 12:00 to 12:53 p.m. (53 minutes), session 12. Client confirmed she was at home in a private room and gave a callback number.
G: Goal 1: improve mood and daily functioning. Objective 1.2: complete 3 planned activities a week. Client completed 0 of 3 planned activities this week and 1 of 3 on average over the last 4 weeks (activity log); no change since session 8. PHQ-9 today 17 (was 16 on 10/12 and 17 on 10/26); item 9 scored 0. Stated: "I plan them in here and then I just don't." On camera from bed, lights off, speech slow, low volume. Mood "stuck," affect flat.
I: Reviewed 4 weeks of logs and PHQ-9 scores with the client and named the lack of progress openly. Explored what has got in the way, using the client's own words. Asked the client for her view of the plan. Shared the option of a medication evaluation and of increasing session frequency, and discussed both (objective 1.2 and plan review).
R: Client identified that the planned activities "felt like chores," and that what she misses most is her choir, which she stopped after her divorce. Agreed that the current objective is not working. Said she would consider a medication evaluation "if you think it might help," and asked how to bring it up with her doctor. Accepted the idea of twice weekly sessions for 4 weeks. Progress on objective 1.2: no change over 4 weeks.
P: Revise the treatment plan this week with the client: replace objective 1.2 with one valued activity a week chosen by the client, first step contacting the choir director. With the client's signed release, send a referral to her primary care provider for a medication evaluation. Increase to twice weekly sessions for 4 weeks, then review. Next session 11/12, telehealth. Repeat PHQ-9 at each session during this period. Safety plan reviewed; client has the 988 Suicide and Crisis Lifeline (call or text 988) on it.
A run of notes that says "no change" is not a problem in itself. A run of notes that says "no change" with the same plan every week is. GIRP makes that pattern easy to see, which is one of its strengths.
When the goal changes
Goals are not fixed for the length of treatment, and GIRP notes should show when they move. Three situations come up often.
- The objective is met. Say so in the Response ("met: 3 of 4 meetings for 3 weeks running"), and name the next objective in the Plan. Update the treatment plan before you start writing notes against a new objective.
- The objective is not moving. After a few sessions of "no change," the Plan should show a change of approach, frequency, level of care, or the objective itself, as in Example 5. Reviewers look for this, and so do good supervisors.
- A new problem appears. If a client brings a new concern that is not in the plan (a bereavement, a new diagnosis, a safety issue), record the session honestly under the closest goal, describe the new concern in the status lines, and add it to the plan at the next opportunity. Do not stretch an unrelated goal for weeks to cover it.
Words to watch in GIRP notes
Progress notes are read by people who were not in the room, and more and more often by clients themselves. A few habits make notes vaguer, more judgmental or less useful than they need to be.
| Instead of | Try | Why |
|---|---|---|
| "Working on goals." | "Objective 2.1: spoke in 1 of 2 meetings (baseline 0 of 4)." | Names the objective and shows where it stands. |
| "Client is doing better." | "Fell asleep alone on 3 of 7 nights, up from 2 of 7 (parent chart)." | Shows the change and how you know. |
| "Client was resistant / unmotivated." | "Client said, 'I plan them in here and then I just don't.'" | Describes behavior instead of labeling the person. |
| "Good progress." | "Progress on objective 1.1: progressing, 3 of 7 nights." | Says which objective and by how much. |
| "Used MI." | "Used importance and confidence rulers; client rated 8 and 4." | Names the actual intervention and the result. |
| "Family is dysfunctional." | "Planning talk ended early when voices were raised over a missing assignment." | Describes what happened, not a judgment of the family. |
| "Client admitted drinking." | "Client reported 4 drinking days this week." | "Admitted" can imply wrongdoing; "reported" is neutral. |
| "Continue treatment." | "Weekly per plan; repeat PHQ-9 at the 12/3 plan review." | Shows why more sessions are needed and how progress is tracked. |
Also watch for copy and paste notes. Copying the goal line forward is exactly what GIRP expects; copying the status, Intervention and Response lines forward is not. If ten notes in a row have identical text under I and R, a reviewer may conclude that nothing individual happened, and a covering clinician cannot tell what changed.
Medical necessity: why GIRP notes help
For insurance funded therapy, each note helps show that the service was needed and that treatment is working, or being changed when it is not. Medicare only pays for services that are "reasonable and necessary for the diagnosis or treatment of illness or injury" (Social Security Act, section 1862(a)(1)(A)), and commercial plans and Medicaid programs use their own medical necessity definitions. The treatment plan is the anchor, and a GIRP note is built to point at it.
Medicare contractors publish documentation expectations for psychotherapy. One billing and coding article (A57065, Outpatient Psychiatry and Psychology Services) says that "the medical record should document the target symptoms, goals of therapy and methods of monitoring outcome," and that "there should be documentation in the medical record of how the treatment is expected to improve the health status or function of the patient." It also says that when services are frequent or long, "the plan of treatment, progress notes, and condition of the patient should justify the intensity of the services rendered." Goals, methods of monitoring and progress are the backbone of a GIRP note.
Another article (A56937, Psychiatry and Psychology Services) lists items that "must be included in all psychiatric medical record documentation and made available upon request," including the name of the beneficiary and date of service, the type of service, the time element where face to face time determines the code, the modalities and frequency of treatment, "a clinical note for each encounter, where in the aggregate, summarizes" diagnosis, symptoms, functional status, focused mental status examination, treatment plan, prognosis and progress to date, and the identity and credentials of the person performing the service.
Time. Individual psychotherapy codes are time based. Medicare billing article A57520 says start and stop times or total times must be documented for 90832, 90834 and 90837, and to choose the code closest to the actual time: 16 to 37 minutes for 90832, 38 to 52 minutes for 90834, and 53 or more minutes for 90837, with no psychotherapy code for under 16 minutes. Commercial payers may apply the same CPT time rules or add their own, so check your contracts.
How the pieces line up in a GIRP note:
- Session details: time, format, type of service and who attended.
- Goal: the documented target and objective, plus current symptoms and functioning with a measure where you use one. This shows the need is still there.
- Intervention: the modality and techniques, tied to the objective. This shows skilled treatment was delivered.
- Response: progress toward the objective. This shows whether treatment is working.
- Plan: frequency and next steps, and changes when progress stalls. This justifies continuing care, or explains a change.
Privacy basics: progress notes, psychotherapy notes, Part 2 and FERPA
Under HIPAA, a GIRP note is a progress note
HIPAA gives extra protection to one narrow category called "psychotherapy notes." The definition in 45 CFR 164.501 covers notes "recorded (in any medium) by a health care provider who is a mental health professional documenting or analyzing the contents of conversation during a private counseling session or a group, joint, or family counseling session and that are separated from the rest of the individual's medical record." The same definition excludes "medication prescription and monitoring, counseling session start and stop times, the modalities and frequencies of treatment furnished, results of clinical tests, and any summary of the following items: Diagnosis, functional status, the treatment plan, symptoms, prognosis, and progress to date."
A GIRP note is mostly made of those excluded items: times, modality, the treatment plan goal, symptoms, measure scores and progress. So it is part of the clinical record, not a psychotherapy note, whatever your software calls it.
- Client access. Under 45 CFR 164.524, individuals have a right to inspect and get a copy of their information in the designated record set, with an exception for psychotherapy notes. Clients can generally ask to see their GIRP notes.
- Authorization. Under 45 CFR 164.508(a)(2), a covered entity must obtain the client's authorization for most uses and disclosures of psychotherapy notes, with narrow exceptions. Progress notes follow the general HIPAA rules for treatment, payment and health care operations.
- Minimum necessary. Under 45 CFR 164.502(b), covered entities must make reasonable efforts to limit uses and disclosures to the minimum necessary for the purpose, with some exceptions such as disclosures to a provider for treatment. In a note, that means describing what matters for care, not everything that was said.
- Keep process notes separate, if you keep them. Personal process notes (hypotheses, your own reactions, verbatim content) only get psychotherapy note protection if they are kept separate from the rest of the record.
HIPAA applies to covered entities, which include health care providers who transmit health information electronically in connection with standard transactions such as claims. A self pay therapist who never bills electronically may not be a covered entity, but state law, licensing board rules and professional ethics codes still govern records.
Substance use disorder records: 42 CFR Part 2
Records from federally assisted programs that provide substance use disorder diagnosis, treatment or referral for treatment are also covered by 42 CFR Part 2. HHS updated Part 2 in a 2024 final rule that aligns parts of it with HIPAA, including allowing a single patient consent for all future uses and disclosures for treatment, payment and health care operations. HHS states that compliance with the updated rule was required by February 16, 2026, and that Part 2 records still cannot be used to investigate or prosecute the patient without written patient consent or a court order. If you work in a Part 2 program, follow your program's consent forms and disclosure procedures.
School counselors: FERPA
The 2019 joint guidance from HHS and the US Department of Education explains that the HIPAA Privacy Rule excludes records protected by FERPA from the definition of protected health information, and that in most cases HIPAA does not apply to an elementary or secondary school's student health records because they are education records under FERPA. FERPA's definition of education records (34 CFR 99.3) excludes records "kept in the sole possession of the maker" that are "used only as a personal memory aid" and not shared with others except a temporary substitute. A GIRP style counseling note that is shared, filed or used for planning will usually not meet that exception. Follow your district's records policy and your state's rules.
Sources for this section: eCFR (45 CFR 164.501, 164.502, 164.508, 164.524; 34 CFR 99.3), HHS Office for Civil Rights mental health and personal representative guidance, HHS 42 CFR Part 2 final rule fact sheet and Part 2 overview, and the HHS and Department of Education joint guidance on HIPAA and FERPA (2019 update). Rules change; check the current versions.
Common GIRP note mistakes
- A goal line with no status. "Goal: reduce anxiety" and nothing else leaves the reader with no picture of the client that day. Add what they reported, what you saw and any measure.
- Goals too vague to measure. If the objective is "feel better," the Response can never say whether it moved. Fix the plan.
- Interventions unrelated to the goal. If the G line names objective 2.1 and the Intervention is about something else entirely, either the wrong goal is named or the plan needs updating.
- Naming the model instead of the intervention. "CBT" or "MI" is a model; "used importance and confidence rulers and reviewed the drinking day as a chain" is an intervention.
- A Response that repeats the Intervention. "Client participated in role play" is not a response. Say what changed, what the client said or did, or that nothing changed.
- No progress line. GIRP's main advantage is the trend across notes. Mark met, progressing, no change or worse every time.
- The same plan after weeks of no change. If the objective is stuck, the Plan should show a change.
- Missing or vague time. Time based codes need start and stop times or total time.
- A risk concern without a plan. If the status lines or Response mention risk, the Plan should show what you did.
- Process material in the record. Your hypotheses and reactions belong in supervision or in separate psychotherapy notes, not in the GIRP note.
Free printable: GIRP note template, filled example and checklist
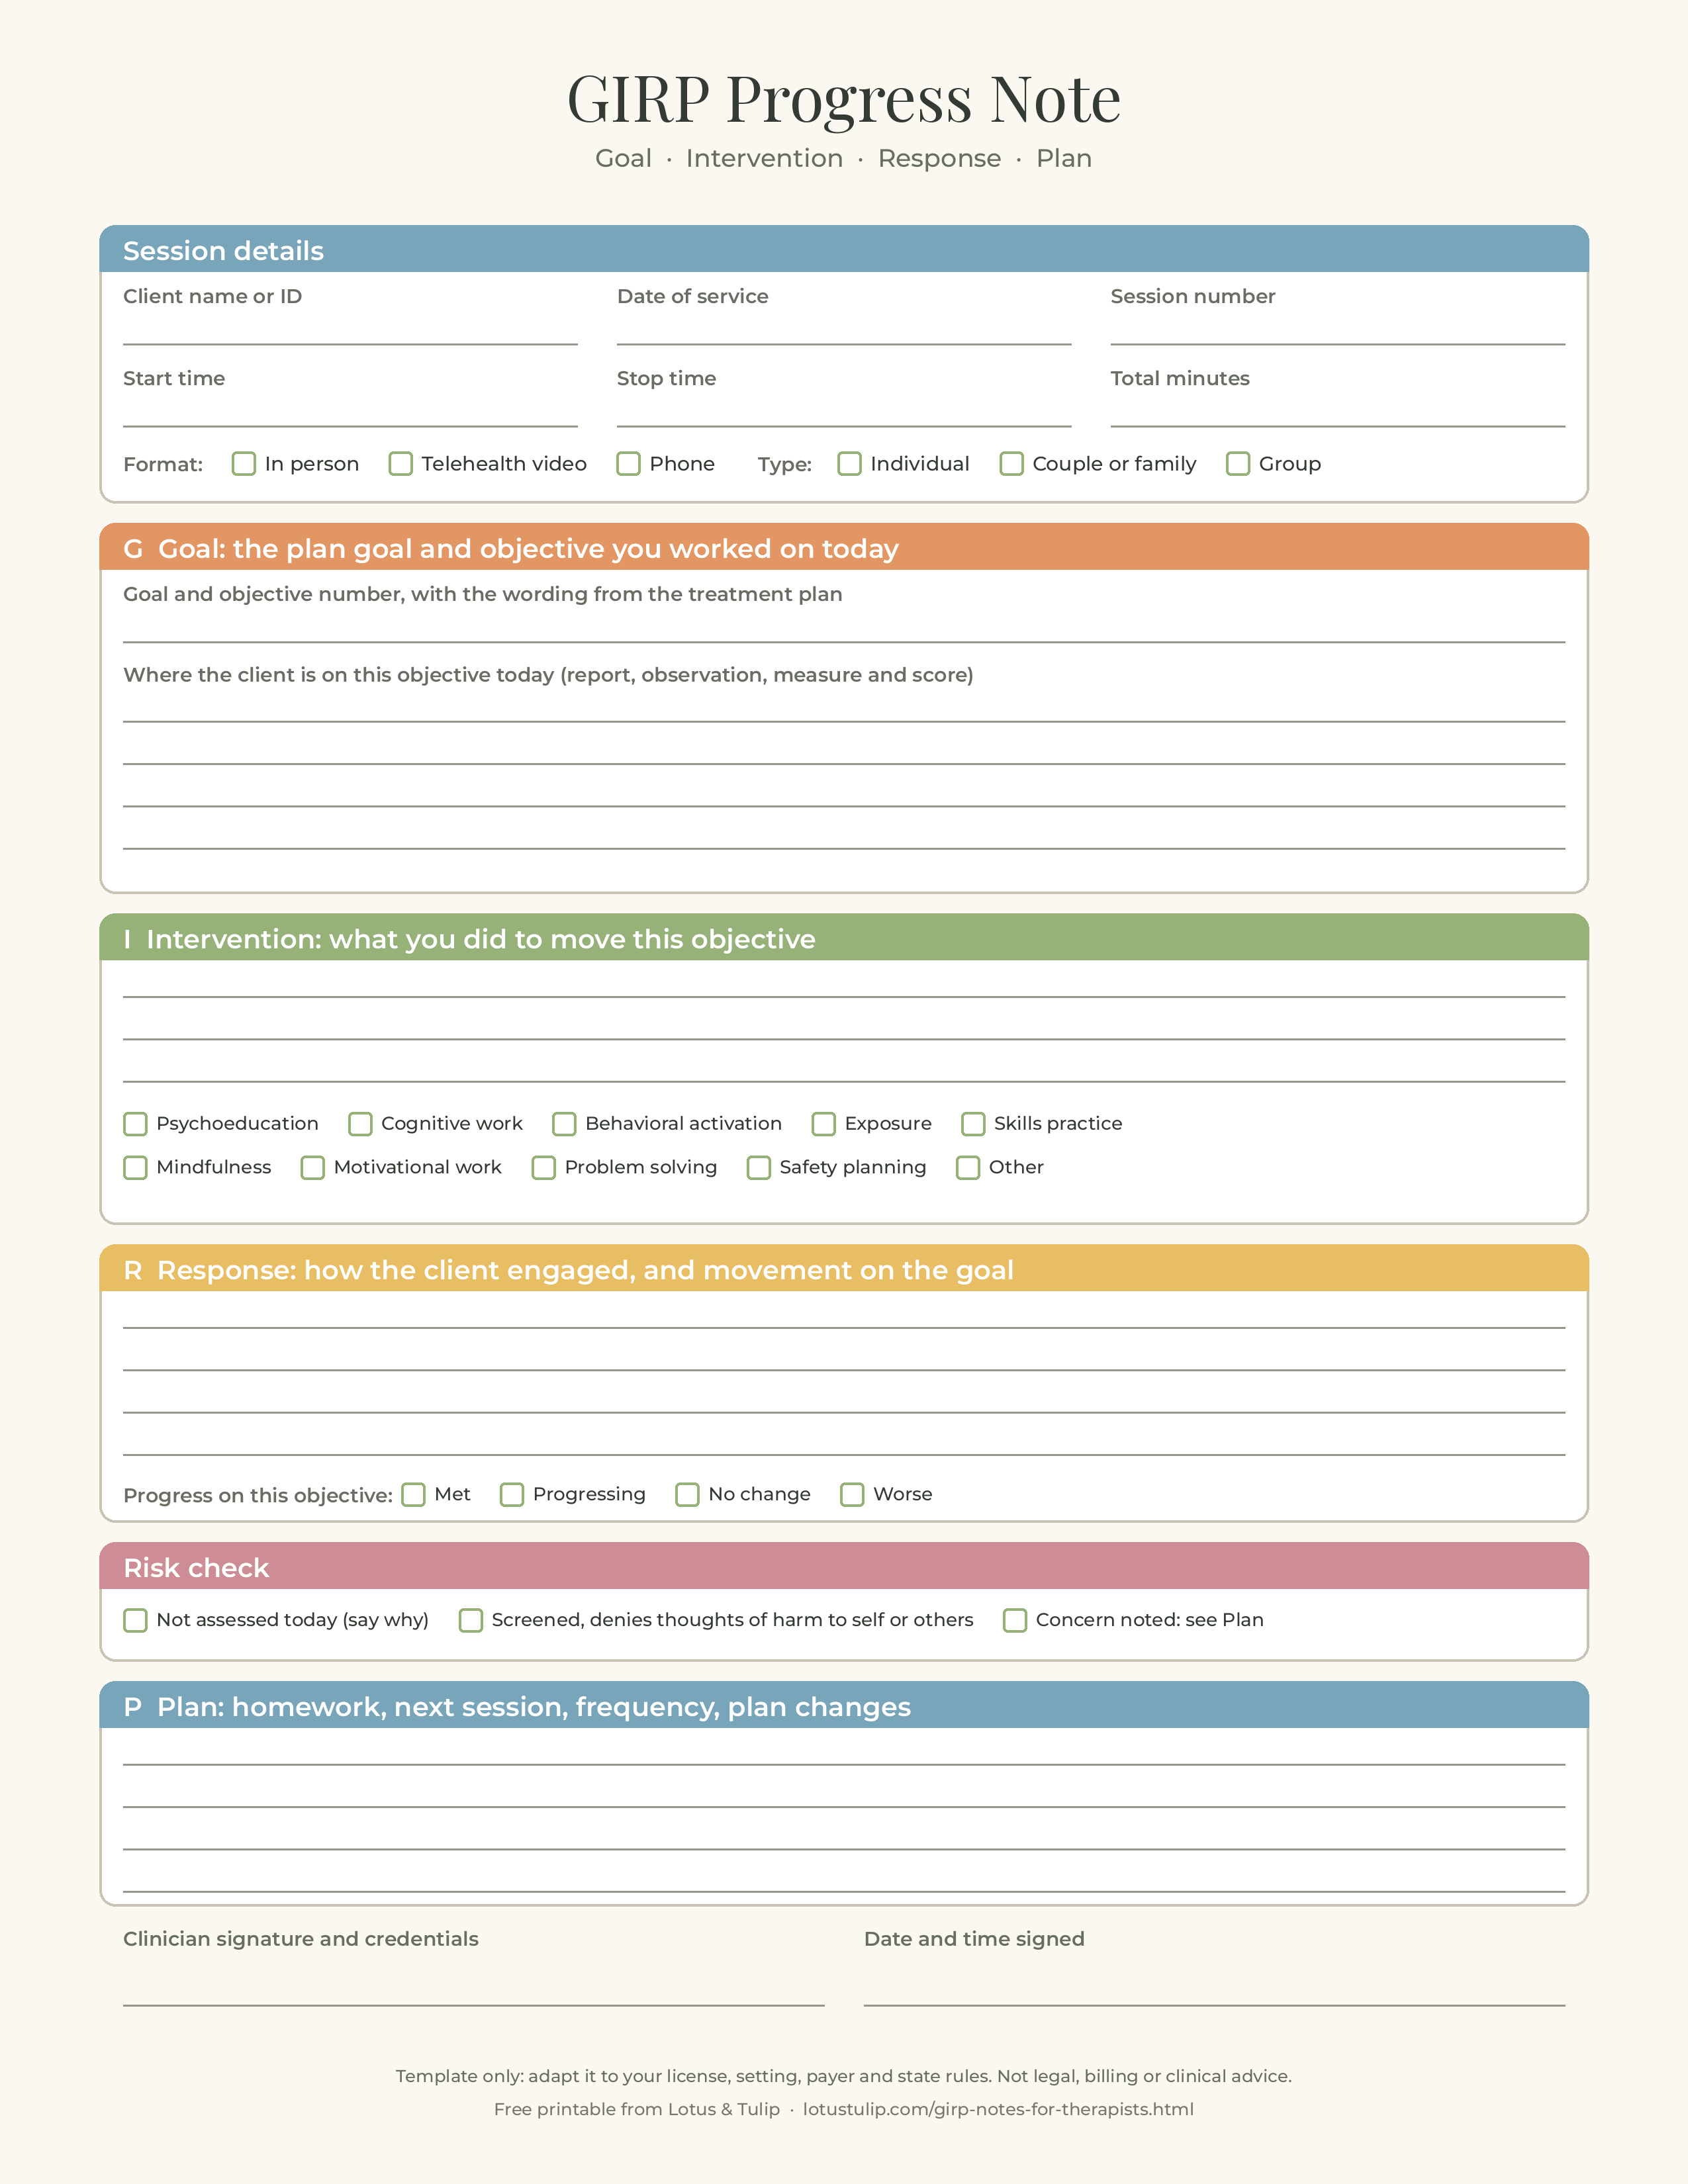
The free printable has three US Letter pages: a blank GIRP note with session details, a Goal section with a line for the plan's goal and objective and lines for the client's status, an Intervention section with an interventions checklist, a Response section with a progress on this objective checkbox (met, progressing, no change, worse), a risk check, a Plan section and a signature line; a filled example for a fictional adult client with social anxiety (Example 1 above); and a one page checklist with twelve checks before you sign, a table that turns vague goals into objectives you can write to, and a short reminder about progress notes and psychotherapy notes.
Download the free GIRP note template (PDF, 3 pages)
Rather type than handwrite? The free PDF above is for printing. Therapy Progress Notes and Intake Templates comes as a fillable PDF you type straight into (604 fields in Adobe Acrobat Reader), plus the printable version: SOAP, DAP and BIRP notes, intake, treatment plan and safety plan, 20 pages. Holiday 20% off: about $7.36, was $9 (EUR 8) · instant digital download
Buy on EtsyPrefer single images? Page 1: blank GIRP note template (PNG) · Page 2: filled GIRP note example (PNG) · Page 3: before you sign checklist and goal to objective table (PNG)
Free to print and use in your own practice. Please link to this page rather than re-uploading the file. The template is a starting point: adapt it to your license, setting, payer and state rules. Using it does not guarantee that any payer, auditor or board will accept your documentation.
Related resources
- Closing a therapy private practice: checklist, timeline, client letters, records plan and free printable
- HIPAA risk assessment for therapists: security risk analysis, filled example and free worksheet
- Business associate agreement for therapists: which vendors need a BAA, breach duties, filled vendor log and free printable
- Professional will for therapists: clinical executor, records custodian, client notification scripts, filled example and free printable
- Couples therapy informed consent form: no secrets policy, individual sessions, records access, safety screening, filled example and free printable
- Treatment summary template for therapists: how to write a treatment summary letter, transfer records under HIPAA, filled example and free printable
- Notice of privacy practices for therapists: HIPAA 164.520 elements, 2026 Part 2 update, filled example and free printable
- Parental consent form for therapy of a minor: who can consent, custody orders, state minor consent laws, HIPAA, filled example and free printable
- Credit card authorization form for therapists: card on file consent, PCI DSS rules, filled example and free printable
- Sliding scale fee policy for therapists: 2026 poverty guideline tiers, copay waiver rules, filled example and free printable
- Therapy cancellation policy template: late cancellation and no show fees, Medicare and Medicaid rules, filled example and free printable
- Release of information form for therapists: HIPAA authorization elements, psychotherapy notes, Part 2, filled example and free printable
- Superbill template for therapists: every field insurers need, CPT and POS codes, filled example and free printable
- Good Faith Estimate template for therapists: No Surprises Act rules, filled example and free printable
- Psychotherapy notes vs progress notes: what HIPAA says, what goes where and free printable
- Therapy termination letter template: how to end therapy ethically, sample letters and free printable
- Informed consent for therapy template: what to include, sample consent and free printable
- Biopsychosocial assessment template: example, 4 Ps formulation and free printable
- BIRP notes for therapists: template, 5 examples and free printable
- Group therapy progress notes: template, examples and free printable
- Therapy discharge summary template: example and free printable
- Telehealth progress note template: examples, checklist and free printable
- Mental status exam template: examples, word bank and free printable
- SOAP vs DAP notes for therapists, with examples
- Therapy treatment plan template with SMART objectives (free printable)
- What to include in a therapy intake form (checklist)
- Therapy progress notes and intake templates
- Safety plan worksheet (free printable)
- Behavioral activation worksheet (free printable)
FAQ
What does GIRP stand for in a progress note?
GIRP stands for Goal, Intervention, Response and Plan. Goal records the treatment plan goal and objective the session addressed and where the client is on it today, Intervention records what you did, Response records how the client responded and their progress on the objective, and Plan records homework, the next session, referrals, safety steps and any change to the plan.
What is the difference between GIRP and BIRP notes?
Only the first section differs. GIRP starts with the treatment plan goal and the client's status on it; BIRP starts with the client's behavior and presentation. A BIRP note with a goal line at the top and a GIRP note with good status lines contain nearly the same information. Use the one your agency or payer asks for, or the one that fits how your sessions usually start.
What is the difference between GIRP and SOAP notes?
SOAP uses Subjective, Objective, Assessment and Plan and comes from the problem oriented medical record in medicine. GIRP is organized around the treatment plan goal and gives the interventions and the client's response their own sections, which makes the therapy work and progress toward the plan easy to see.
What goes in the Goal section of a GIRP note?
Two things: the goal and objective from the treatment plan, by number and in the plan's wording, and the client's current status on it. Status means what the client reported since last session, what you observed, and any measure given today with its score and a comparison score.
Can a GIRP note cover more than one goal?
Yes. Name each goal or objective you worked on in the Goal section, and make sure the Intervention and Response sections say which work served which objective, with a progress line for each. For group sessions, see the group therapy progress notes guide.
How long should a GIRP note be?
Long enough that another clinician could continue the work and a reviewer could see why the session was needed, which is often a few lines per section. There is no single required length; follow your agency and payer requirements.
Are GIRP notes psychotherapy notes under HIPAA?
No. The HIPAA definition of psychotherapy notes in 45 CFR 164.501 covers notes about the contents of counseling conversations that are kept separate from the medical record, and it excludes session times, modalities, test results and summaries of diagnosis, symptoms, functional status, the treatment plan, prognosis and progress. A GIRP note contains those items, so it is part of the clinical record, which clients generally have a right to see.
Is this GIRP note template free?
Yes. The three page printable (blank GIRP note, filled example and checklist) is free to print and use in your own practice. Please link to this page rather than re-uploading the file, and adapt it to your setting and payer requirements.